

Retinal detachment
When vitreoretinal traction must be relieved and the retina repaired through a vitreous approach.
Vitrectomy is microsurgery involving the vitreous and retina. Depending on indications, the surgeon removes opacities and traction, treats the retina and uses gas or silicone tamponade.
When vitreoretinal traction must be relieved and the retina repaired through a vitreous approach.
For persistent, recurrent or clinically significant haemorrhage, especially if it limits retinal treatment.
Traction, non-clearing vitreous hemorrhage, tractional detachment or macular threat.
When indicated to relieve traction and support hole closure.
With significant symptoms and anatomy when expected benefit justifies surgical risk.
Intraocular foreign body, lens/IOL dislocation, endophthalmitis and other complex indications selected by the surgeon.
Do not apply another patient’s recovery times, head positioning or restrictions to yourself: they depend on the individual operation.
Vitrectomy is intraocular surgery with real risks and must not be presented as risk-free or guaranteed to restore vision.
Anatomical success, such as retinal reattachment, does not guarantee a specific visual-acuity outcome.
With intraocular gas, air travel and major altitude changes are prohibited until full absorption; nitrous oxide/Entonox is also dangerous.
Postoperative head positioning is individualized; universal face-down positioning is incorrect.
Silicone oil requires a separate removal operation; the surgeon determines the timing.
The first step before planned vitrectomy is a vitreoretinal surgeon consultation confirming the indication and surgical goal.
Tell the team about diabetes, anticoagulants/antiplatelets, allergies, cardiovascular disease and other chronic conditions.
If gas tamponade may be used, discuss flight, altitude and nitrous-oxide anesthesia restrictions in advance.
Anatomical success—such as retinal reattachment—does not guarantee the restoration of visual acuity. While an intraocular gas bubble is present, air travel and significant elevation gain are prohibited until it is completely resorbed; nitrous oxide/Entonox is also hazardous. Postoperative head positioning is prescribed individually. "Face-down positioning for all patients" is an incorrect generalization. Silicone oil requires a separate surgical procedure for removal; the timing is determined by the surgeon.
Book a consultation
Vitreoretinal examination, review of OCT/ultrasound/other data and definition of the surgical goal.

Testing and medical clearance according to KazRIED protocol and anesthesia risk.

Small scleral access ports are created for instruments in the vitreous cavity.
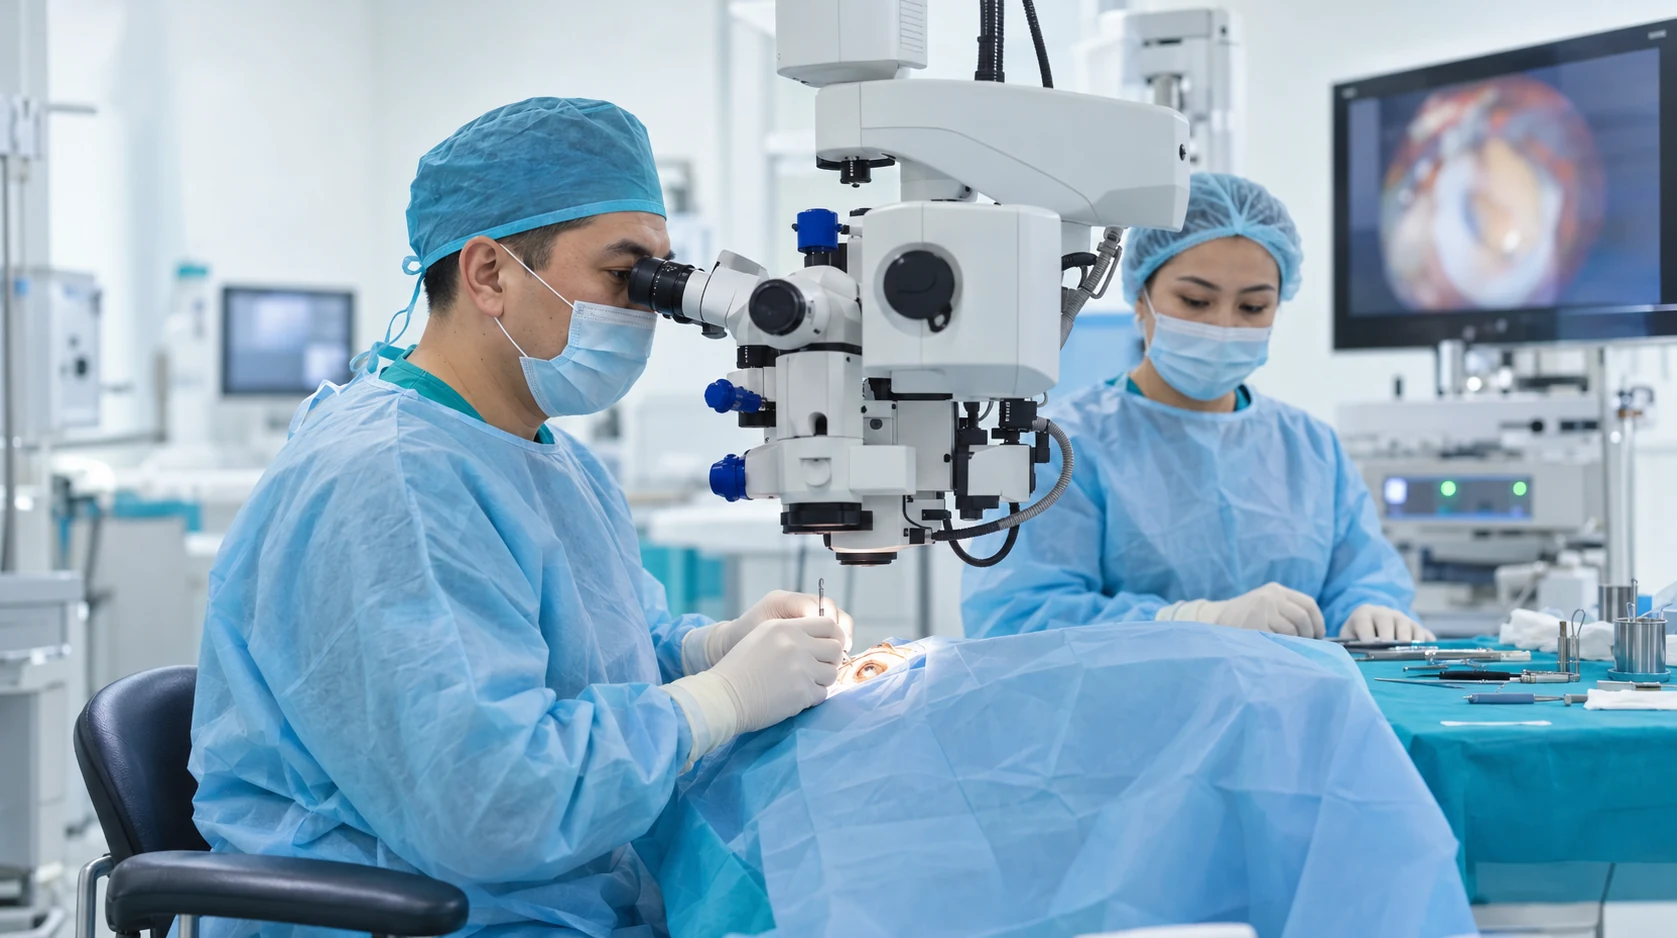
Pathologic vitreous is removed and retinal traction is relieved.
As indicated: membrane peeling, endolaser, retinal manipulation and other steps.
Gas or silicone oil is used when needed; the choice depends on the surgical goal.
Drops, positioning, restrictions and follow-up are individualized.

Vitrectomy allows removal of blood or abnormal vitreous that obstructs light and retinal treatment.
The surgeon can remove bands and membranes that pull on the retina and distort its position or shape.
Vitreoretinal surgery makes it possible to treat changes that cannot be addressed with drops or external laser alone.
In complex disease, laser treatment can complement other indicated retinal treatments.
The pathway to vitrectomy starts with a vitreoretinal surgeon consultation. Report urgent warning symptoms when booking so the clinic can determine the appropriate timing of assessment.
A team of experienced doctors across specialties.

Doctor of Medical Sciences; Highest-category ophthalmologist
Candidate of Medical Sciences, Associate Professor; Highest-category ophthalmologist

Doctor of Philosophy (PhD)

Highest-category ophthalmologist

Highest-category ophthalmologist

First-category ophthalmologist

First-category ophthalmologist

Second-category ophthalmologist; PhD Degree Candidate


Prices are per eye, per operation. The vitreoretinal surgeon selects the procedure. Confirm tariff contents, including anaesthesia, materials and additional stages, with the clinic.
Vitrectomy is surgery involving the vitreous and retina, with its extent determined by the underlying condition. The surgeon removes abnormal vitreous and performs additional steps when needed.
The operation may include removal of tractional or epiretinal membranes, retinal endolaser treatment, retinal flattening, and gas or silicone oil tamponade.
At KazRIED, vitrectomy is used to treat vitreous and retinal conditions when observation, laser treatment, or injections are insufficient or do not address the mechanical problem.
After consultation and diagnostic assessment, the vitreoretinal surgeon determines the extent of vitreous removal, the need for membrane and retinal work, and the use of endolaser and tamponade.
If a cataract is also present, separate or combined surgery is discussed.
Postoperative instructions and the follow-up plan are individualized.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


