


Astigmatism
Suspected progressive keratoconus. Vision is changing, astigmatism is increasing, spectacle prescriptions change frequently, or serial examinations show changes in corneal shape or thickness.
Treatment for keratoconus and other corneal diseases depends on the cause, stage and progression. Goals may include improving vision, stopping progression or replacing damaged tissue.
Suspected progressive keratoconus. Vision is changing, astigmatism is increasing, spectacle prescriptions change frequently, or serial examinations show changes in corneal shape or thickness.
Corneal ectasia after refractive surgery. Corneal thinning or abnormal protrusion has been identified after laser vision correction and a cornea-specific treatment plan is required.
Irregular astigmatism with poor spectacle correction. Conventional glasses do not provide sufficient image quality because of corneal irregularity, and specialised contact correction including individual or scleral lens fitting needs assessment.
Recurrent erosion or superficial opacity. Painful epithelial episodes recur or a superficial lesion is present for which therapeutic PTK may be considered after examination.
Keratitis, corneal ulcer or marked inflammation. Pain, photophobia, redness, reduced vision or a corneal lesion requires assessment of the cause and targeted treatment.
Corneal dystrophy, oedema or loss of transparency. The layer and depth of disease, endothelial status and the appropriate medical or surgical pathway need to be determined.
Scar, severe deformation or major structural damage. An ophthalmic surgeon should assess reconstructive options and, when indicated, the current transplantation pathway.
Cross-linking is not prescribed solely because keratoconus has been diagnosed. The decision depends on documented change, corneal thickness and condition, scarring, age and other clinical factors. Scleral lenses may improve optical quality but do not stop progressive ectasia. PTK is intended for selected superficial corneal pathology and is not a universal treatment for keratoconus.
Bring previous corneal topography or tomography, pachymetry , surgical records, and older spectacle or contact-lens prescriptions. Comparing serial tests is particularly useful when progression of keratoconus is suspected.
Tell the ophthalmologist about previous eye surgery or trauma, herpes-related eye disease, allergy, frequent eye rubbing and systemic conditions that may affect the cornea.
Provide a complete list of eye drops and systemic medicines you use regularly. Do not stop prescribed treatment on your own before the visit.
If you wear contact lenses, ask KazRIED in advance whether they should be removed before topography or tomography and for how long.
The interval depends on lens type and the diagnostic protocol.
Eye pain , marked photophobia, sudden visual loss, pronounced redness, chemical exposure or trauma require prompt in-person assessment rather than routine self-treatment.
Prompt in-person ophthalmic assessment is required for sudden severe pain, marked photophobia, rapidly reduced vision, a white or grey corneal spot, chemical injury, penetrating trauma, or a painful red eye in a contact-lens wearer. In keratoconus, sudden marked blur with corneal swelling may represent acute hydrops. This page does not confirm that KazRIED provides 24-hour emergency care.
Prompt in-person ophthalmic assessment is required for sudden severe pain, marked photophobia, rapidly reduced vision, a white or grey corneal spot, chemical injury, penetrating trauma, or a painful red eye in a contact-lens wearer. In keratoconus, sudden marked blur with corneal swelling may represent acute hydrops. This page does not confirm that KazRIED provides 24-hour emergency care.
Book a consultation
The ophthalmologist reviews symptoms, visual change, previous prescriptions, contact-lens use, surgery, trauma, allergy and inflammatory episodes.

Transparency, surface condition, scarring, inflammation, erosions and other anterior-segment findings are assessed.

When indicated, corneal topography or tomography, pachymetry, endothelial microscopy and other tests are performed.
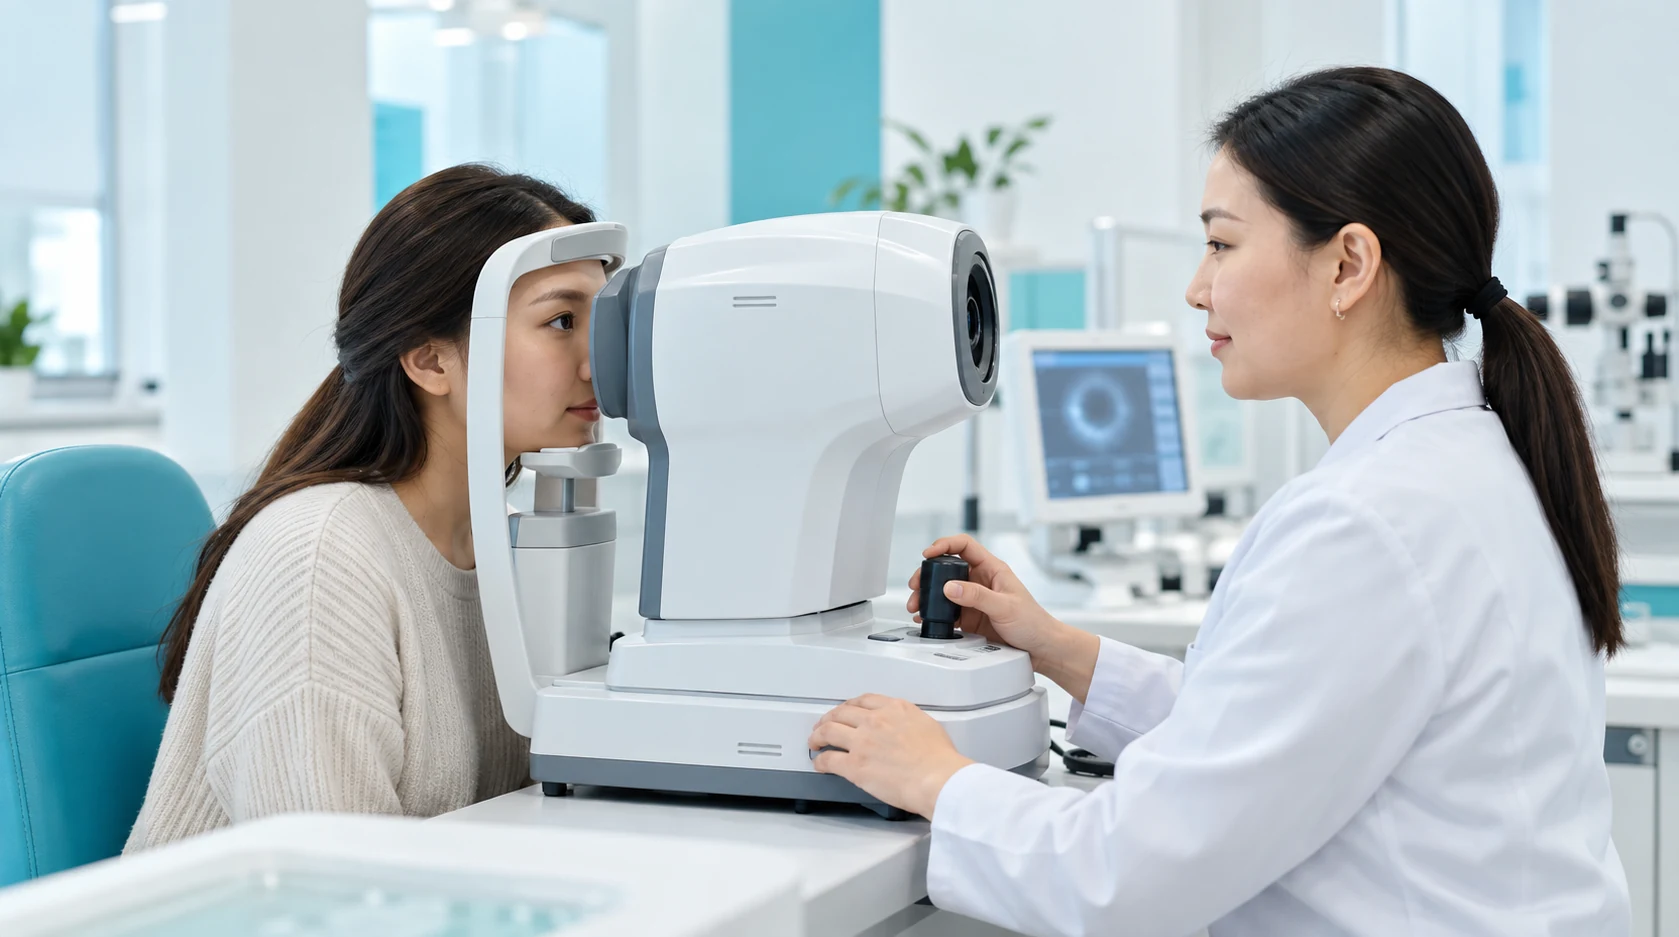
The clinician separates disease stabilisation from optical rehabilitation, treatment of a superficial lesion, or surgical reconstruction.

Cross-linking, PTK, contact-lens correction, medical therapy or a surgical pathway is chosen only when the findings support it.
Repeat testing depends on diagnosis, method and progression risk; comparable serial studies matter in keratoconus.

Treatment is selected according to the cause, stage and depth of the corneal condition.
In progressive ectasia, cross-linking aims to strengthen the cornea and slow further changes.
Glasses or specialist contact lenses are selected according to corneal shape and achievable visual acuity.
Assessing the depth of changes helps select an appropriate method, including lamellar or full-thickness transplantation when indicated.
Cross-linking strengthens the cornea using riboflavin and controlled UV-A exposure.
Learn moreBook a consultation and cornea-focused diagnostic assessment at KazRIED. After examination, the ophthalmologist can determine whether the priority is keratoconus stabilisation, a therapeutic procedure, optical rehabilitation or another treatment pathway.
A team of experienced doctors across specialties.

Doctor of Medical Sciences, Associate Professor; Highest-category ophthalmologist

Candidate of Medical Sciences; Highest-category ophthalmologist

Candidate of Medical Sciences; Highest-category ophthalmologist
Master’s Student in Public Health

Highest-category ophthalmologist

Highest-category ophthalmologist

Highest-category ophthalmologist

Highest-category ophthalmologist

Highest-category ophthalmologist
Highest-category ophthalmologist
The cornea is the transparent front part of the eye and one of its main refractive structures. Corneal diseases may alter its shape, reduce transparency, cause inflammation, and damage different layers: the epithelium, stroma, or endothelium.
Treatment therefore depends on the diagnosis, depth of involvement, corneal thickness and shape, scarring, inflammation, and changes over time.
In keratoconus, the cornea becomes thinner, more protruding, and asymmetric. This causes irregular astigmatism, distorted images, glare, and reduced visual quality.
Stopping progression and improving image quality are different goals.
Optical correction does not replace treatment to control progression. Glasses or contact lenses may still be needed after cross-linking.
If glasses no longer provide adequate image quality because of irregular astigmatism, a specialist assesses suitability for specialty lenses.
For certain superficial conditions and some corneal opacities, the clinician may consider phototherapeutic keratectomy (PTK).
This is a therapeutic excimer laser treatment of the cornea. PTK differs from refractive PRK and TransPRK and does not primarily aim to correct myopia or astigmatism.
PTK does not replace cross-linking: these methods serve different treatment goals.
For keratitis, ulcers, and other inflammatory conditions, the cause is established first. Treatment targets the infectious, inflammatory, or other underlying mechanism.
If infection is suspected, the clinician may request microbiological testing of ocular discharge before or during treatment. This is performed when indicated and is not mandatory for every patient.
Deep scars, severe dystrophies, or significant structural damage require surgical assessment. The clinician evaluates the feasibility of reconstructive surgery, including keratoplasty, and the available treatment pathway.
When the source material was prepared, KazRIED’s official website reported that corneal transplantation at the institute was temporarily suspended because of legislative changes. Current availability must be confirmed.
Suspected ectasia after refractive surgery requires corneal tomography and a separate management plan. Routine repeat laser correction should not be considered an automatic solution.
Corneal endothelial microscopy is also listed among the examinations; the specific device model is not stated.
The frequency of follow-up depends on the diagnosis, chosen treatment, and risk of progression. In keratoconus, comparing consistent examinations over time is particularly important.
Individual price-list items should not automatically be added together as a “treatment package.” The total depends on the consultation, diagnostic testing, treatment procedure, and optical correction when needed.
The listed fees do not automatically represent the full cost of a treatment course.
At KazRIED, the pathway is selected after a specialist assessment. The first step is to establish the diagnosis, affected layer and depth, disease progression, and main treatment goal.
This helps build a sequential plan: corneal stabilization, treatment of a specific condition, visual rehabilitation, or surgical reconstruction.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


