

Intraocular pressure
Target IOP is not achieved with maximally tolerated therapy. A lower target IOP is required in advanced glaucoma. Laser treatment has not produced sufficient and durable pressure reduction.
Trabeculectomy creates an additional route for aqueous outflow to lower eye pressure. It is planned for glaucoma according to target pressure, progression risk and healing considerations.
Target IOP is not achieved with maximally tolerated therapy. A lower target IOP is required in advanced glaucoma. Laser treatment has not produced sufficient and durable pressure reduction.
Visual field or optic nerve damage progresses despite treatment.
Drops are poorly tolerated or do not provide reliable control of progression risk.
Glaucoma and cataract coexist and a combined procedure is being considered.
Trabeculectomy is intraocular surgery and carries a risk of intraoperative and postoperative complications.
Depending on the clinical situation, additional treatment may be required, including laser suture lysis, injections of medication into the filtering bleb area, bleb revision, resumption of pressure-lowering medication or repeat glaucoma surgery.
Bring tonometry, gonioscopy, visual-field, optic nerve/RNFL OCT and pachymetry results and previous treatment records. Do not stop glaucoma drops, anticoagulants or systemic medicines on your own.
Before surgery, the doctor reviews the ocular surface and conjunctiva, previous operations, inflammation, injuries, cataract, systemic conditions and medicines that may affect bleeding or healing.
Patients should seek immediate medical attention for severe pain, sudden loss of visual acuity, marked eye redness, purulent discharge or other warning symptoms specified by their surgeon.
Trabeculectomy is an intraocular surgical procedure and carries a risk of intraoperative and postoperative complications. Possible complications include hypotony or insufficient reduction in intraocular pressure, a shallow anterior chamber, excessive filtration of aqueous humour from the filtering bleb, inflammatory reactions, intraocular haemorrhage, choroidal detachment, cataract progression, scarring of the filtering bleb and infectious complications.
Book a consultation
The doctor assesses glaucoma type and stage, target pressure and surgical risk.

Preparation and anaesthesia according to the KazRIED protocol.

Conjunctival access and creation of a partial-thickness scleral flap.
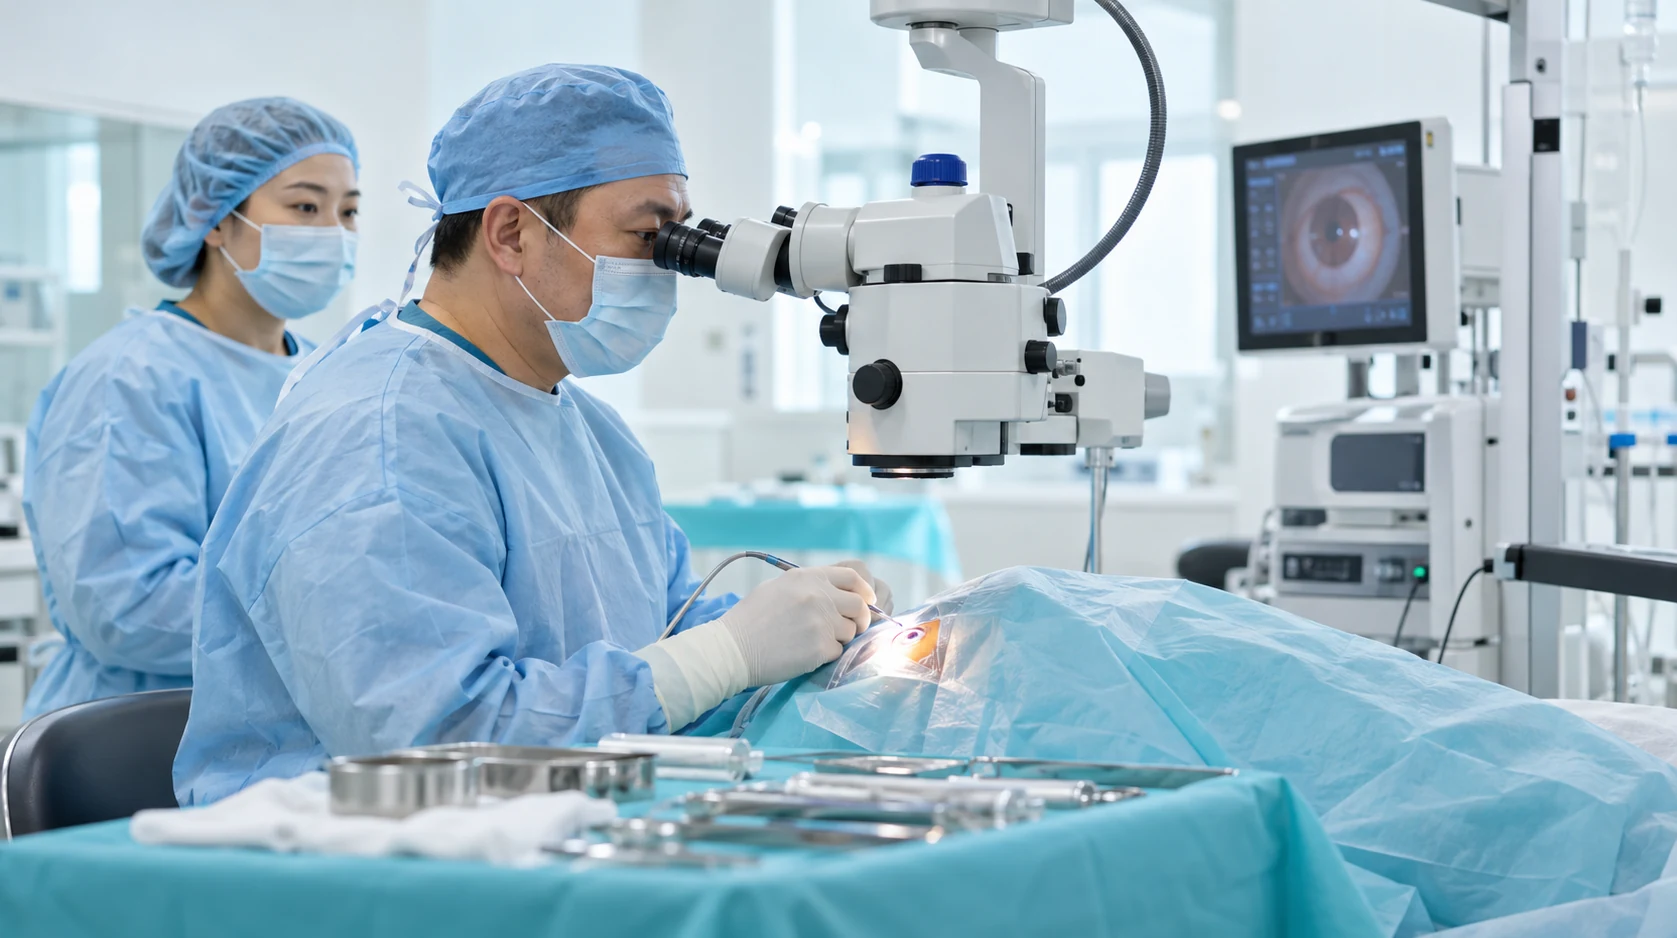
Controlled entry into the anterior chamber and creation of a filtration pathway.
Peripheral iridectomy and an antifibrotic strategy when indicated.
Fixation of the scleral flap, watertight conjunctival closure and initial filtration assessment.
Postoperative reviews of IOP and bleb function with management adjusted to healing.

Trabeculectomy creates an additional route for aqueous fluid drainage to lower pressure.
The surgical approach is selected according to the pressure needed to protect the individual optic nerve.
When indicated, the doctor may consider a combined surgical approach for glaucoma and cataract.
Scheduled examinations allow healing and pressure to be monitored and treatment adjusted when needed.
The surgeon will review target IOP, rate of progression, visual fields, optic nerve OCT, tolerance of drops, response to laser treatment and conjunctival status, then determine whether trabeculectomy or another operation is more appropriate.
A team of experienced doctors across specialties.

Candidate of Medical Sciences; Highest-category ophthalmologist

Candidate of Medical Sciences; Highest-category ophthalmologist

Candidate of Medical Sciences; Highest-category ophthalmologist

Candidate of Medical Sciences; Highest-category ophthalmologist

Highest-category ophthalmologist

Highest-category ophthalmologist

Highest-category ophthalmologist

First-category ophthalmologist
Second-category ophthalmologist

Second-category ophthalmologist
Trabeculectomy is a filtering procedure for glaucoma. During surgery, the surgeon creates a new controlled pathway for aqueous humor to drain beneath the conjunctiva.
The surgeon creates a partial-thickness scleral flap and an opening into the anterior chamber, allowing aqueous humor to drain into the subconjunctival space. A filtering bleb forms over the filtration site.
The outcome depends on both surgical technique and tissue healing. Excessive scarring can reduce filtration, making postoperative examinations an essential part of treatment.
In selected cases, the surgeon may use anti-scarring medications or drainage materials. The specific approach is determined individually.
Trabeculectomy is considered when the required intraocular pressure (IOP) level and the risk of progression justify filtering surgery.
Depending on the clinical situation, laser treatment, nonpenetrating deep sclerectomy (NPDS), a glaucoma drainage device, or combined surgery with cataract removal may be more appropriate.
For patients with both glaucoma and cataract, KazRIED lists cataract phacoemulsification combined with trabeculectomy as a separate tariff item.
The operation does not restore visual field that has already been lost. Its purpose is to reduce the risk of further glaucoma progression.
The main measure of success is safely lowering IOP to an individualized target and preserving the remaining optic nerve function over time. Sharper vision the next day is not the primary measure of surgical effectiveness.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


