

Macular region
Patients in whom the ophthalmologist needs to clarify the vascular component of retinal, macular or peripapillary abnormalities or monitor known disease over time.
OCT angiography images ocular vascular structures without injected contrast dye. It complements other tests, with interpretation taking scan quality and method limitations into account.
Patients in whom the ophthalmologist needs to clarify the vascular component of retinal, macular or peripapillary abnormalities or monitor known disease over time.
When indicated: neovascular AMD and other macular neovascularization, diabetic retinopathy, retinal vascular occlusions, myopic neovascularization, selected vascular/inflammatory disorders and adjunct assessment in glaucoma.
Quality may fall with poor fixation, motion, nystagmus, cataract or other media opacity, hemorrhage, marked edema or distorted anatomy. Motion, projection, segmentation and shadowing artifacts can occur; very slow flow can fall below the detection threshold.
A special diet or fasting is usually unnecessary for OCT angiography itself because no intravenous dye is injected.
During scanning, you need to fixate on a target for several seconds and avoid blinking when possible. Poor fixation can reduce image quality and create artifacts.
Contact lenses are not usually a primary limitation for OCTA, but removal may be requested if other diagnostic tests are performed during the same visit.
Reduced central vision, distortion of straight lines, a central spot, new visual distortion or a change in a known disease may prompt an examination. These symptoms are not automatic indications specifically for OCTA; the physician selects the method.
Vessel density, perfusion density and other automated metrics depend on manufacturer, algorithm, scan area and image quality. Values from different platforms are not fully interchangeable.
The device and software color maps do not make a diagnosis by themselves. A physician interprets the result in the context of examination, structural OCT and other tests.
A red, dark or absent area on a map does not automatically equal disease. It can reflect true pathology, shadowing, motion, segmentation error or flow below the system detection threshold.
OCTA does not show vascular leakage. When leakage and filling phases are clinically important, FA may be indicated.
In glaucoma, OCTA does not replace tonometry, optic nerve head assessment, RNFL/GCC analysis, visual field testing, gonioscopy when indicated or comprehensive ophthalmic interpretation.
No intravenous contrast injection is needed. Bring previous images and treatment information. The team will tell you whether pupil dilation is required.
Pupil dilation is not always technically required for OCTA. The decision depends on pupil size, signal quality, examination purpose and the physician’s assessment.
Bring previous OCT/OCTA images, ophthalmology reports and discharge summaries. If you are receiving retinal treatment , provide dates of intravitreal injections, including anti-VEGF therapy.
Sudden vision loss , a new curtain-like shadow, a marked increase in floaters/flashes, severe pain, trauma or intense redness requires urgent clinical assessment rather than only a routine OCTA appointment. Sudden vision loss, a curtain-like defect, many new floaters or flashes, severe pain, trauma, marked redness or rapid deterioration requires urgent clinical evaluation.
OCTA may be only one part of that work-up.
The device and software color maps do not make a diagnosis by themselves. A physician interprets the result in the context of examination, structural OCT and other tests.
Book a consultation
The physician clarifies symptoms, diagnosis and the purpose of imaging, such as detecting/monitoring macular neovascularization, assessing diabetic capillary changes or comparing findings after treatment.
Takes: 1 min

The patient is seated at the tomograph with chin and forehead supported.
Takes: 1 min

The patient fixates on the target.
Takes: 1 min
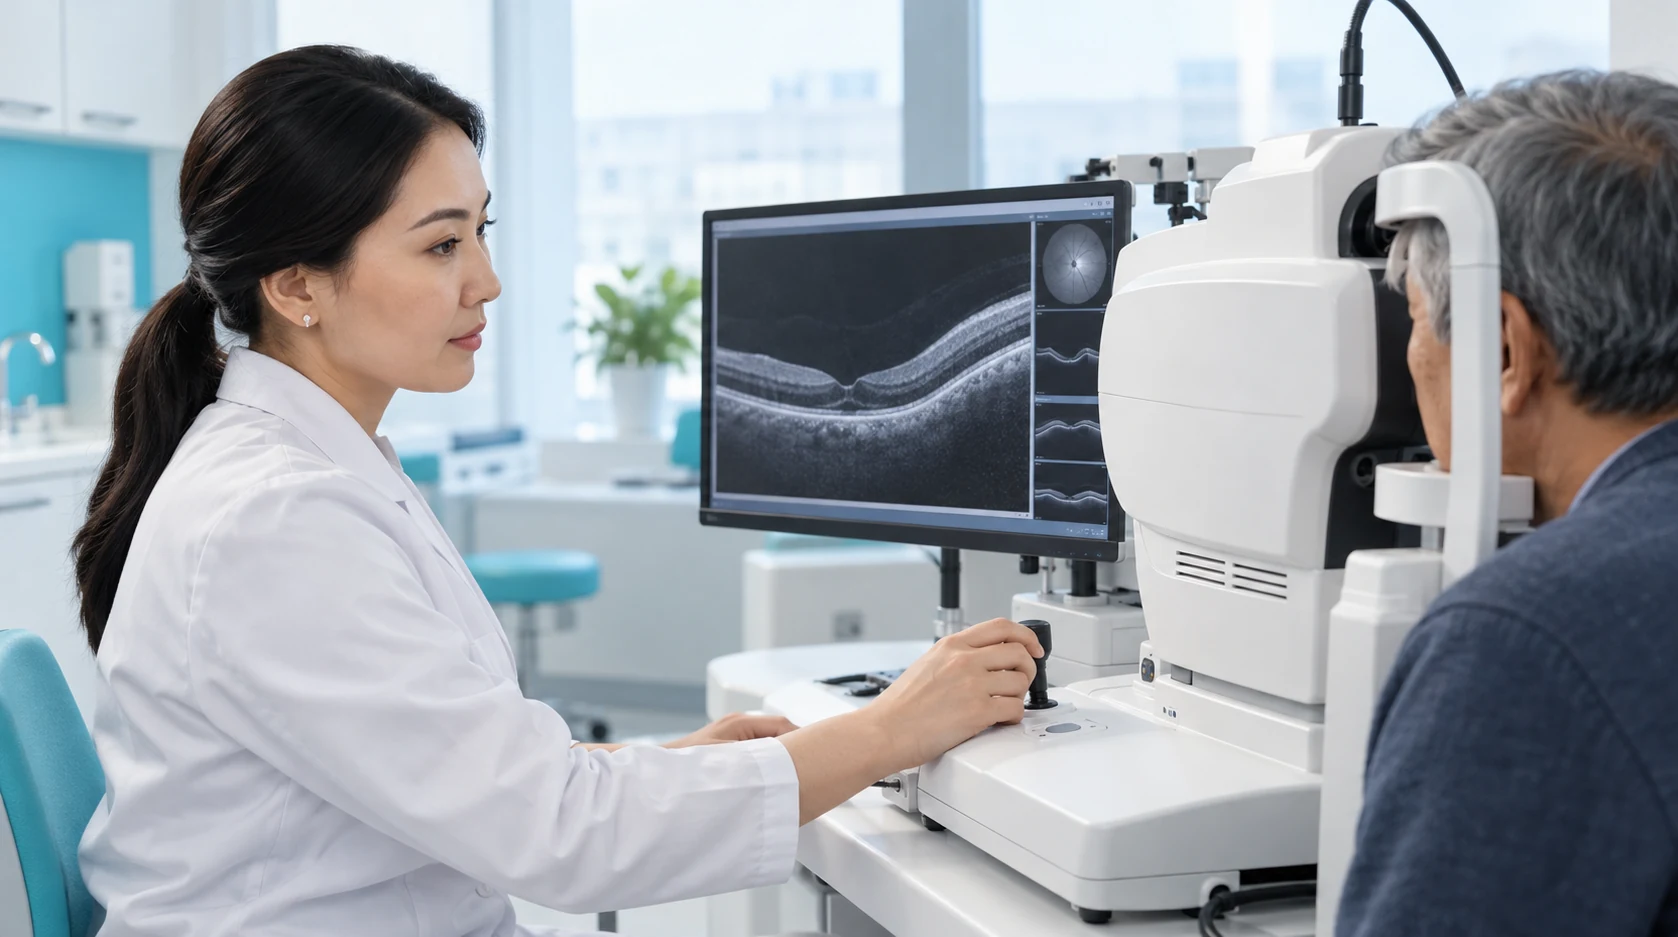
Signal, fixation and visible artifacts are reviewed.
Takes: 1 min

The physician correlates en face maps with flow overlay on B-scans, checks segmentation and compares the result with structural OCT, prior studies and the clinical examination.
Takes: 5 min
OCT angiography helps assess vascular networks in selected retinal layers and other accessible areas.
OCT angiography shows vascular networks without fluorescein injection, supporting repeat monitoring when needed.
Vascular maps are compared with OCT cross-sections to locate changes within the tissues.
Comparable repeat examinations reveal changes and help assess prescribed treatment.
If the physician needs to assess the retinal or macular vascular network without intravenous dye, OCTA may be part of the diagnostic pathway. When booking, confirm the branch, current price and whether a specialist ophthalmologist consultation is required before or after imaging.
OCT angiography and fluorescein angiography prices are per eye.
Structural OCT pricing depends on the area and protocol; separate tariffs are in the price table.
A team of experienced doctors across specialties.

Highest-category ophthalmologist

Highest-category ophthalmologist


OCT angiography uses a sequence of rapidly repeated optical scans.
When the reflected signal changes because blood cells are moving, the software detects that change and builds a vascular map.
Therefore, the medically accurate wording is that OCTA assesses vascular architecture and detectable blood-cell motion signal; it does not universally measure absolute blood flow in milliliters or directly provide blood velocity as a physical quantity.
Structural OCT shows anatomy: retinal thickness, fluid, edema, atrophy, and the condition of the macula and optic nerve. OCTA shows vascular patterns in selected layers.
In clinical practice, the physician usually compares both parts of the examination because a vascular map without structural B-scans may be misinterpreted when artifacts or segmentation errors are present.
OCTA may be useful in macular neovascularization, diabetic retinopathy, retinal vascular occlusions and selected other conditions. In glaucoma it is an adjunct tool for microvascular assessment rather than a stand-alone diagnostic test.
The main distinction from fluorescein angiography is that OCTA does not require intravenous fluorescein and can display depth-resolved vascular layers. However, it does not show vascular leakage or reproduce dye transit phases. For some clinical questions, the physician may order FA in addition to OCTA rather than choose one method as a universal replacement for the other.
The device detects optical-signal changes associated with moving blood cells and creates depth-resolved vascular maps.
For the patient, the practical value is that the physician can correlate vascular architecture with structural OCT and decide whether observation, additional angiography or disease-specific treatment is needed.
Preparation for scanning
The patient is seated at the tomograph with chin and forehead supported. Pupil dilation is performed only if required by the examination protocol.
Repeated scan acquisition
The patient fixates on a target while the device repeats B-scans of the same region to identify optical-signal changes related to moving blood cells.
Quality control
Signal, fixation and visible artifacts are reviewed. If image quality is inadequate, selected scans may be repeated.
The physician correlates the result with symptoms and other tests. A normal OCTA map does not exclude every eye disorder or cancel follow-up required for a known condition.
Structural OCT and clinical activity are reviewed, then the physician decides whether observation, additional tests or treatment is needed.
Image quality, B-scan, shadowing, segmentation and the possibility of very slow flow are checked before a clinical conclusion is made.
The scan may be repeated or an alternative/complementary test may be recommended if fixation, media opacity or anatomy prevents a reliable vascular map.
For longitudinal comparison, use the same scan region and platform when possible. Repeat treatment decisions should not be based on a single OCTA metric but on the complete clinical picture.
The OCTA result is more than a single “vessel picture.” Depending on the device and protocol, the physician may receive en face maps of selected vascular layers, source structural B-scans with flow overlay and software-derived quantitative indices. These data must be checked for artifacts and interpreted together.
The practical outcome for the patient is more than a printout:
it answers the next clinical questions.
This approach reduces the risk of mistaking an automated device map for a final diagnosis.
Related information: Glaucoma.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


