

Glaucoma and suspected glaucoma
Standard automated perimetry is used to assess functional damage and monitor changes in the visual field.
Perimetry tests the visual field and helps identify areas of reduced sensitivity. The doctor interprets the result alongside test reliability and other examination findings.
Standard automated perimetry is used to assess functional damage and monitor changes in the visual field.
If a person notices a dark area, tunnel-like vision, part of the image missing or difficulty orienting to the side, the doctor may prescribe visual-field testing.
Perimetry helps quantify defects in optic neuropathies, neuritis, ischemic damage and optic nerve atrophy.
When a lesion of the optic chiasm or visual pathways is suspected, after stroke, or with tumours and other neurological processes, the visual-field map helps localize the functional defect.
When indicated, perimetry is used to assess functional field loss in certain retinal dystrophies and other retinal disorders.
Repeat tests using the same strategy allow visual fields to be compared over time. A comparable protocol and sufficient examination quality are especially important for trend analysis.
Each eye is tested separately. Look at the fixation target and press the button only when you actually see the light stimulus; do not try to guess stimuli.
Poor fixation, high false-positive response rates, fatigue, ptosis, the edge of a corrective lens, markedly reduced vision and other factors can distort the map.
Progression cannot be assessed from a single “worse-looking” map. Monitoring requires comparable tests, quality analysis and a series of observations.
MD, PSD, VFI and equivalent indices depend on the platform and selected strategy. Their meaning and thresholds cannot be transferred mechanically between different instruments and programs.
The perimeter does not establish a diagnosis automatically. A visual-field map is a functional result that the doctor interprets together with the examination and other investigations. A high false-positive rate can make the visual field appear artificially better.
The first threshold test may differ from subsequent tests because of the learning effect. If a result does not fit the clinical picture or quality is low, the doctor may order a repeat examination.
False-negative responses and fixation losses are also assessed, but interpreted in the context of defect severity and patient behaviour.
Normal perimetry does not exclude every eye or optic nerve disorder.
In glaucoma, structural and functional changes are assessed together.
Special preparation is usually unnecessary. Bring your glasses and previous visual-field results, and try not to attend when very tired.
Pupil dilation is usually unnecessary for perimetry. If your pupils have been dilated for another test, agree the timing with the specialist because changes in pupil size and optical correction may affect the result.
No fasting or special diet is required for perimetry itself. Preparation may differ if other examinations are scheduled during the same visit.
Bring your distance and/or reading glasses if you use them, as well as previous visual-field printouts. Appropriate refractive correction can be important for threshold perimetry.
Tell the specialist if you are very tired, unwell, have marked eye pain or dryness, or find it difficult to maintain fixation. These factors may increase test variability.
Sudden loss of half the visual field, a new curtain, sudden visual deterioration, weakness or numbness on one side of the body, speech disturbance or severe headache requires urgent medical assessment rather than scheduled perimetry.
Sudden loss of part of the visual field, particularly with neurological symptoms, flashes, a curtain-like shadow, pain or a sudden reduction in vision, requires urgent assessment.
The perimeter does not establish a diagnosis automatically. A visual-field map is a functional result that the doctor interprets together with the examination and other investigations.
Book a consultation
The doctor or diagnostic specialist determines the purpose: glaucoma monitoring, searching for a neurological defect, assessment of the optic nerve or retina, or another clinical situation.
Takes: 1 min

The team checks which eye is being examined and whether optical correction is needed for the test distance, positions the head correctly and explains how to respond.
Takes: 1 min

The patient looks at the central target.
Takes: 15 min
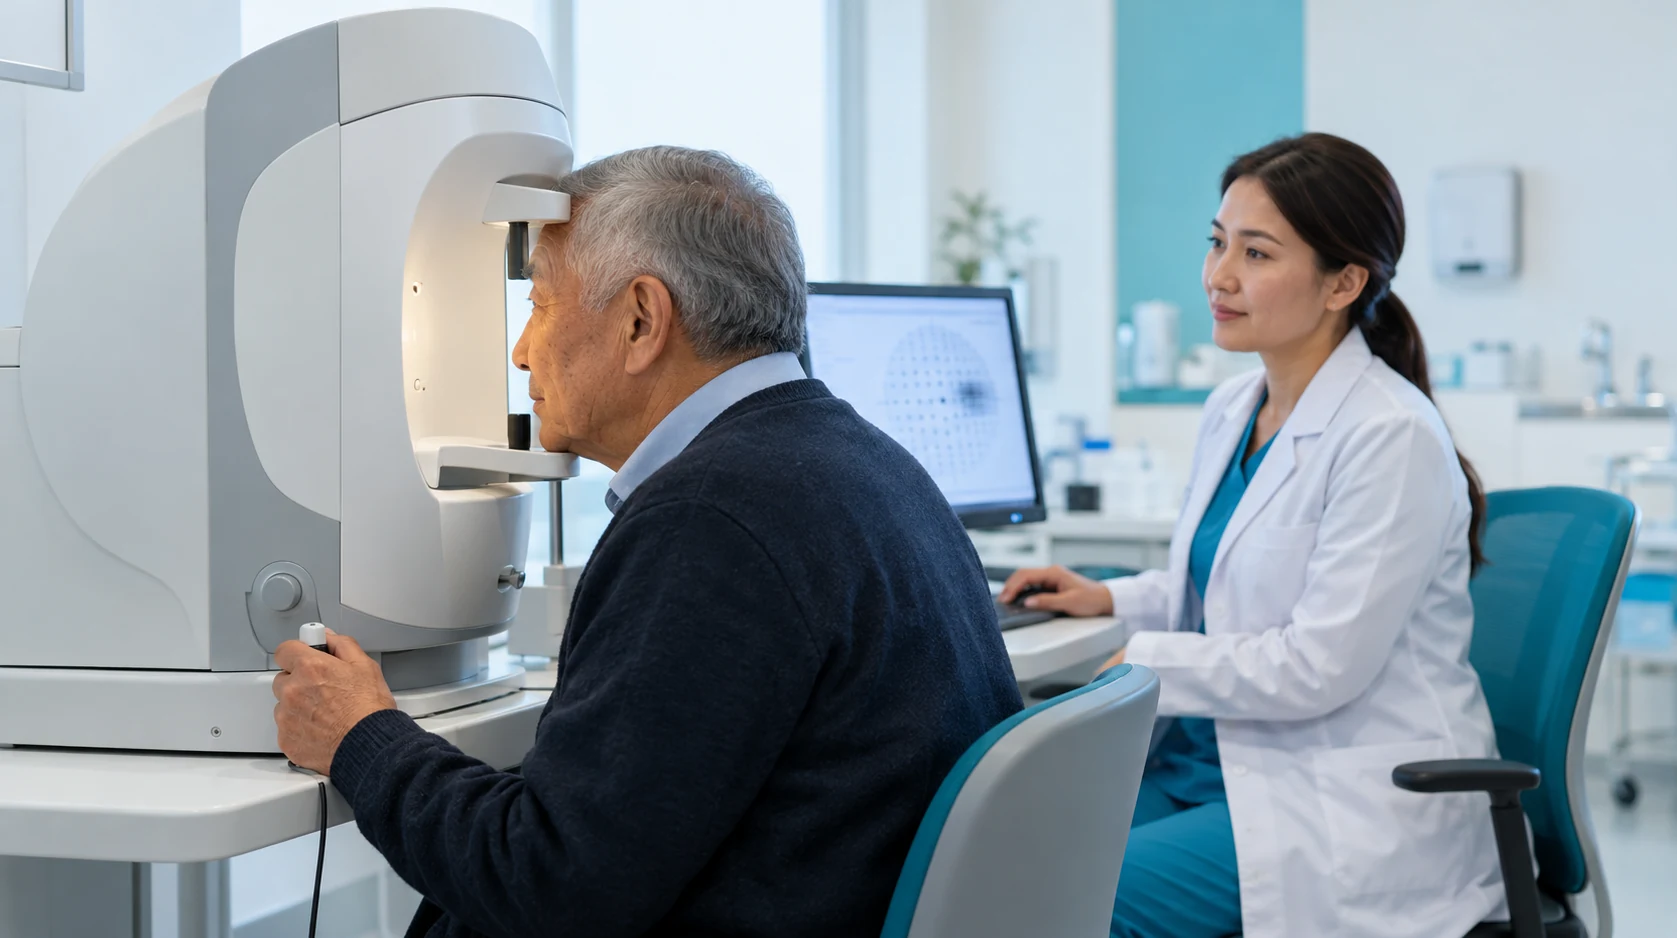
The procedure is repeated for the second eye according to the selected protocol.
Takes: 15 min
The specialist assesses fixation, false-positive and false-negative responses, gaze and patient behaviour, and other signs of reliability.
Takes: 2 min

The ophthalmologist analyses the map and global and local indices, comparing them with previous tests, OCT, intraocular pressure, optic-disc examination and the clinical objective.
Takes: 5 min
Perimetry shows how a person detects objects in central and peripheral vision.
Testing helps detect functional deficits that visual acuity alone cannot describe.
Comparable repeat measurements help the doctor detect deterioration or stability.
Changes in measurements help determine whether treatment is sufficient or needs review.
Book perimetry if it has been prescribed by your ophthalmologist or if functional assessment is needed for glaucoma, optic nerve, retinal or visual pathway disease. If visual-field loss appeared suddenly, mention this when contacting the clinic because urgent assessment may be required.
A team of experienced doctors across specialties.

Highest-category ophthalmologist

Highest-category ophthalmologist

Highest-category ophthalmologist

Highest-category ophthalmologist

Highest-category ophthalmologist

Second-category ophthalmologist


The visual field is the area a person can see while keeping their gaze fixed.
Perimetry does not measure how small a line of letters a patient can read on an eye chart. It assesses a different function: where, and with what sensitivity, the visual system detects a light stimulus.
The test measures light sensitivity at different points in the central and peripheral visual field. It helps identify localized areas of visual field loss, called scotomas, narrowing of the visual field, and characteristic patterns of impairment.
In static computerized perimetry, light stimuli appear at predefined locations and vary in brightness. Based on the patient’s responses, the software estimates the threshold of light sensitivity and produces a visual field map.
In kinetic perimetry, a stimulus moves from an area where the patient cannot see it into an area where it becomes visible. This helps define the boundaries of the visual field and its isopters — lines connecting points of equal light sensitivity.
The method is selected according to the clinical purpose of the examination.
In glaucoma, perimetry reveals functional changes and helps detect and monitor characteristic visual field defects.
However, a diagnosis is not based on a single visual field test. The findings are assessed alongside intraocular pressure, the appearance of the optic disc, optical coherence tomography (OCT) results — including assessment of the retinal nerve fiber layer (RNFL) and ganglion cell complex (GCC) — gonioscopy when indicated, and other clinical findings.
Perimetry is also used in conditions affecting the optic nerve and visual pathways, certain retinal diseases, and following neurological events. The pattern of a defect may help the clinician identify the location of damage, but the visual field map alone cannot establish its cause without clinical context.
Perimetry is a psychophysical test. Its results depend not only on the equipment but also on the patient’s fixation, attention, and responses.
The clinician therefore assesses test reliability and possible artifacts. When necessary, the examination is repeated using a comparable protocol.
The patient receives a visual field map, while the clinician obtains quantitative data to support diagnosis and monitor changes over time.
First-eye testing
The patient looks at the central target. Light stimuli appear at different points, and the patient presses the button when they actually notice them.
Examination of the second eye
The procedure is repeated for the second eye according to the selected protocol. Duration depends on the strategy, number of test points and the patient’s ability to maintain attention.
The physician compares the visual field with other findings. A normal map does not cancel follow-up when risk factors or structural abnormalities remain.
Test quality and anatomical/clinical plausibility are checked first. The field may be repeated or additional tests may be ordered.
The specialist may repeat instructions, improve positioning or optical correction, or choose another strategy/program.
Comparable test strategies are preferred. The physician reviews the sequence of fields, not only the current printout.
The field pattern may prompt neurological assessment and CNS imaging when clinically indicated.
Perimetry may be combined with OCT, fundus photography and other tests depending on the suspected retinal location and disease.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


