

Corneal thickness
Documented progressive keratoconus shown by serial changes in corneal shape, refraction, thickness, or visual function.
Cross-linking strengthens the cornea using riboflavin and controlled UV-A exposure. It is considered to limit keratoconus progression after assessing indications, corneal thickness and contraindications.
Documented progressive keratoconus shown by serial changes in corneal shape, refraction, thickness, or visual function.
Corneal ectasia after refractive surgery: progressive pathological bulging of the cornea has been detected after LASIK, PRK or another procedure. Pellucid marginal degeneration or another progressive ectatic disorder where corneal anatomy and treatment zone are suitable. In keratoconus, mechanical surface trauma is considered a factor that may contribute to progression.
Keratoglobus or complex ectasia: keratoglobus is included among the indications in KazRIED’s official description, but the specific approach requires an individual assessment of corneal thickness and safety.
A young patient with rapidly changing corneal parameters: the higher risk of progression makes timely repeat assessment and a decision on stabilization especially important.
A patient who still obtains useful correction with spectacles or contact lenses but whose ectasia continues to progress: CXL aims to stabilize the cornea, while visual correction remains a separate stage.
Do not rub your eyes.
Plan a safe journey home after the procedure because vision may temporarily be blurred and light sensitivity increased.
intolerance to riboflavin (vitamin B2);
corneal thickness below 400 μm in at least one measurement;
low corrected visual acuity in keratoconus despite sufficient corneal thickness;
allergic conjunctivitis.
Additional caution is required with active infection, significant scarring, poor epithelial healing, severe ocular-surface disease and certain autoimmune conditions. Increasing pain or redness, purulent discharge or a sudden decline in vision after treatment requires an unscheduled examination.
List all eye and systemic medicines you use.
Do not stop prescribed treatment on your own.
Bring previous corneal topography or tomography maps, pachymetry results, old spectacle prescriptions, and contact lens data. Serial results are especially valuable for documenting progression.
Tell the doctor about prior laser vision correction , radial keratotomy, eye trauma, herpetic eye disease, allergies, autoimmune conditions, severe dry eye, or previous epithelial healing problems.
If you wear contact lenses, ask in advance when to remove them before topography or tomography. Timing depends on lens type and the diagnostic protocol.
Cross-linking is not prescribed automatically on the basis of a diagnosis alone.
Book a consultation
The clinician reviews symptoms, prior prescriptions, and serial imaging to determine whether progression is present.

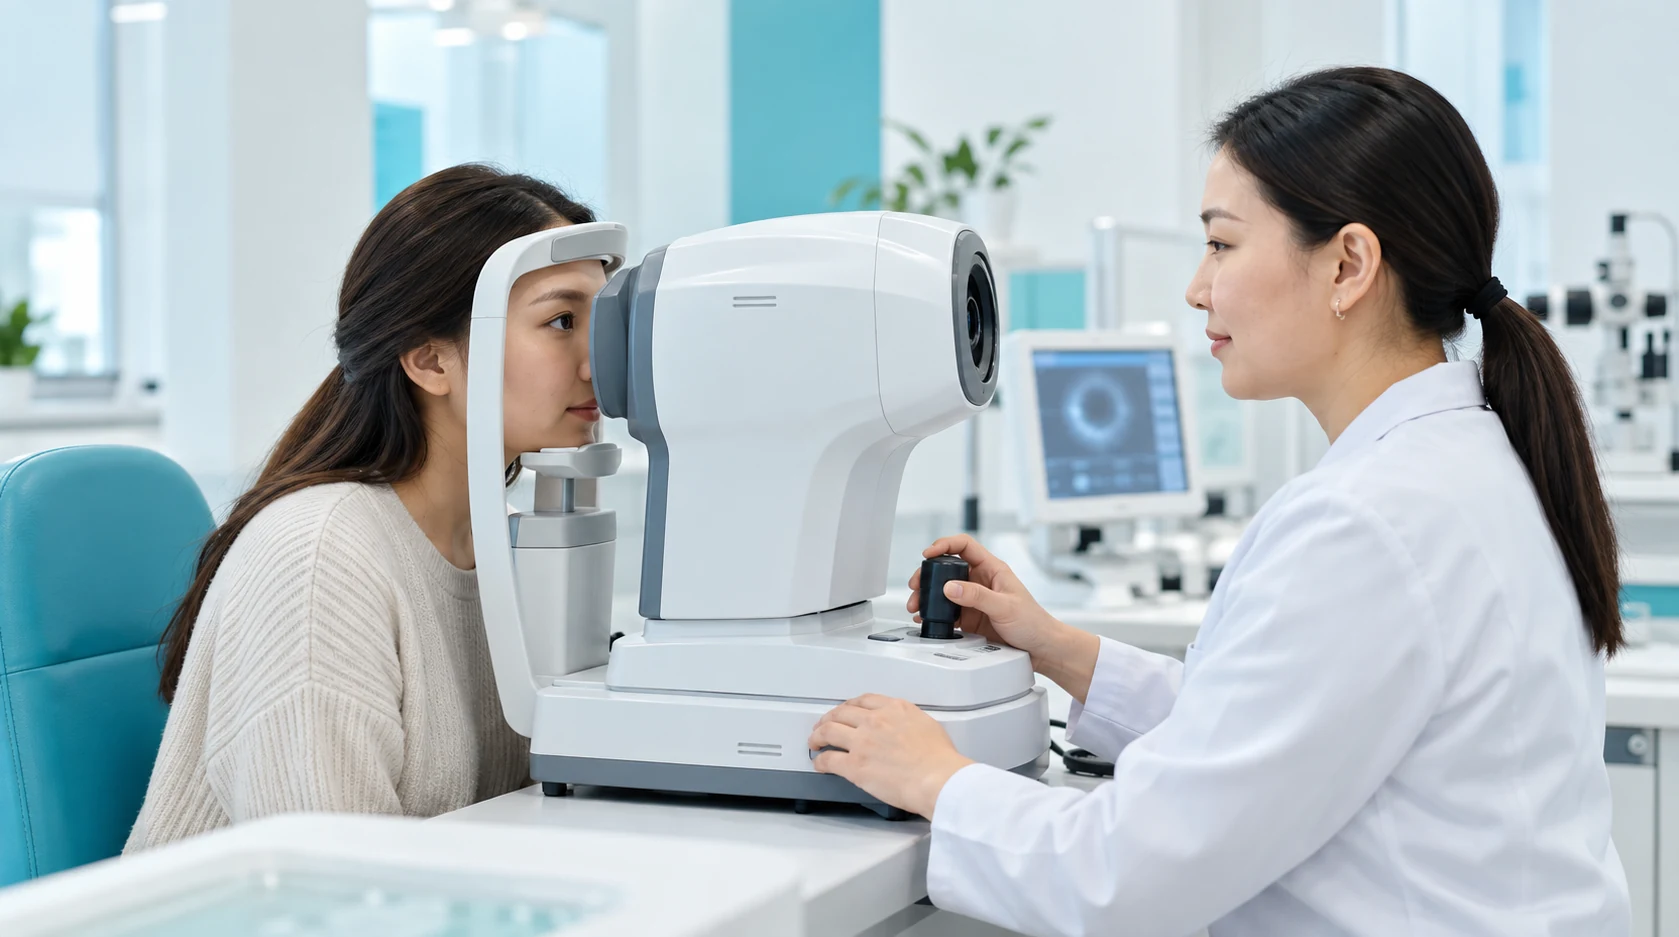
Corneal biomechanics, shape and thickness are assessed, including topography or tomography and pachymetry as indicated.
KazRIED’s service page describes anesthetic eye drops.

In the current KazRIED isotonic CXL description, the epithelium is removed to improve riboflavin penetration.

KazRIED describes 15–30 minutes of riboflavin instillation until adequate tissue saturation is achieved.
The doctor individually selects UV-A mode, power and exposure duration.
The surface is checked during healing, and later serial corneal measurements are compared to determine whether ectasia has stabilized.

In progressive ectasia, cross-linking aims to strengthen the cornea and slow further changes.
Cross-linking treats corneal tissue without replacing it with a donor graft.
Stabilising the condition helps plan optical correction; improved visual acuity is not a guaranteed result of the procedure.
Repeat investigations allow corneal stability and the need to adjust treatment to be assessed.
Book a KazRIED consultation to assess keratoconus progression, corneal shape and thickness, and whether cross-linking is indicated. The treating physician selects the protocol after examination.
A team of experienced doctors across specialties.

Candidate of Medical Sciences; Highest-category ophthalmologist
Highest-category ophthalmologist

Highest-category ophthalmologist

Highest-category ophthalmologist
Corneal cross-linking changes the cornea’s biomechanical properties to improve its stability. It is not intended to reshape the cornea by ablation or eliminate refractive error.
Riboflavin acts as a photosensitizer, while controlled UV-A exposure triggers photochemical reactions that increase cross-links within the corneal collagen structure.
In progressive keratoconus and other ectatic conditions, the main goal is to stop or slow documented progression, improve corneal biomechanical stability, and reduce the risk of further deformation and thinning.
Before treatment, it is important to confirm the diagnosis and assess changes in corneal shape and thickness over time.
If keratoconus is newly diagnosed but the measurements remain stable, the clinician may recommend monitoring rather than immediate intervention.
The standard epi-off approach involves temporary removal of the central epithelium to improve riboflavin penetration. Professional sources regard it as the most extensively studied and predictable approach for progressive ectasia.
Transepithelial and individualized protocols also exist, but their effectiveness and indications depend on the specific technology.
For a very thin cornea or significant scarring, the standard isotonic protocol may be unsuitable. Further management is determined by a specialist surgeon.
Cross-linking and vision correction serve different purposes. Strengthening the cornea may stabilize the disease, but it does not automatically create an optically regular surface or guarantee improved visual acuity.
Blurred vision after treatment does not, by itself, mean that stabilization has failed. Glasses, rigid contact lenses, or scleral lenses may be needed to improve image quality.
Cross-linking should not automatically be considered preparation for conventional laser vision correction.
After the early recovery period, the clinician assesses visual acuity and the stability of corneal topography or tomography findings.
If corneal measurements continue to change, the clinician reassesses progression, adherence to recommendations, ocular surface condition, and the need for an alternative or repeat procedure.
The decision for the other eye is made separately, based on its own measurements and changes over time.
Once stability has been assessed, further visual rehabilitation is discussed: glasses, contact or scleral lenses, and, in selected clinical situations, other surgical methods.
The availability of intrastromal corneal ring segment implantation at KazRIED requires separate confirmation. It should not be presented as a currently confirmed service without clarification.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


