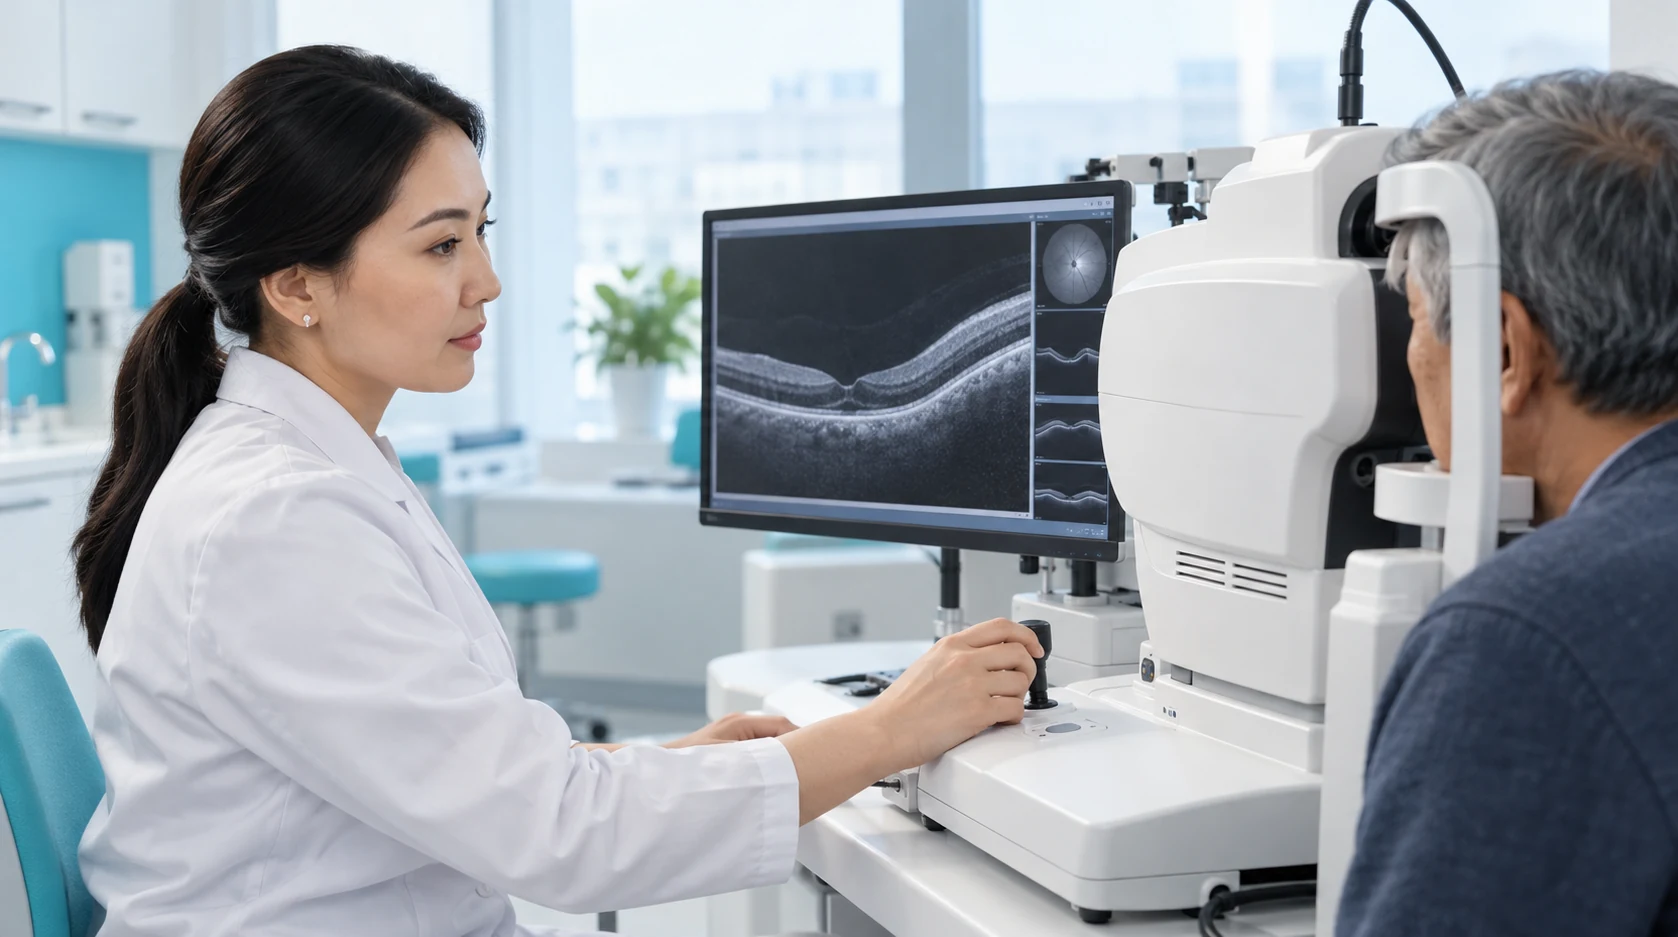
OCT produces cross-sectional images of eye structures without surgery. The scan area is selected for the clinical question, and results are interpreted alongside examination and other tests.
Who the service is for
OCT may be indicated for
OCT may be indicated for reduced central vision; distorted straight lines; a central visual-field spot; suspected macular oedema; age-related macular degeneration; diabetic retinopathy; epiretinal membrane; vitreomacular traction; macular hole; glaucoma or suspected glaucoma; optic nerve disease; monitoring after treatment; or assessing disease progression.
Monitoring with OCT
When prescribed by an ophthalmologist, OCT may monitor patients with glaucoma or suspected glaucoma; age-related macular degeneration; diabetic retinopathy; macular oedema; after intravitreal treatment or retinal surgery; with optic nerve disease; epiretinal membrane; or vitreomacular changes.
Keeping the gaze fixed
For good images, maintain fixation, avoid eye movements where possible and follow the specialist's instructions.
Symptoms that may require examination
Reduced visual acuity; distorted images; straight lines appearing curved; a central spot or darkness; difficulty reading; reduced contrast; unexplained visual deterioration; visual-field changes; or symptoms with diagnosed glaucoma or retinal disease. The doctor determines whether OCT specifically is needed.
How scanning works
The device optically scans the area without surgery or ionising radiation.
What matters for the examination
Optical coherence tomography provides cross-sectional and layered images of eye tissues with high spatial resolution.
OCT quality
OCT quality may be reduced by marked corneal opacity; significant cataract; vitreous opacities; poor fixation; pronounced nystagmus; inability to remain still; a very low-quality optical signal; or scanning artefacts. Poor image quality may require a repeat examination.
Sudden Drop in Vision
In case of a sudden sharp drop in vision; the appearance of a "curtain" or "veil"; a new large number of flashes; a sudden onset of many "floaters"; or pronounced pain;
Glaucoma and eye pressure
OCT is not a standalone diagnostic test for glaucoma.
Optic nerve
For glaucoma diagnosis, OCT is compared with optic-disc findings, intraocular pressure, the visual field and other data.
Visual field
OCT does not show the functional visual field as perimetry does.
Interpreting results
A normal OCT does not exclude all eye diseases. A red or yellow area on a printout is not a diagnosis. Built-in normative databases have limitations.
Individual treatment choice
The clinical significance of the device’s colour maps cannot be determined without a doctor. OCT angiography does not completely replace fluorescein angiography in all clinical situations. Treatment decisions are not based on a single OCT image.
Myopia
In high myopia, anatomical disc variations and other conditions, automated analysis may require especially cautious interpretation.
Assessment before choosing treatment
In some cases, the doctor may recommend pupil-dilating drops for image quality or an additional ophthalmic examination.
Preparing for the service
Special preparation is usually unnecessary.
Results and medical records
Bring previous reports and images if you have had OCT before.
Monitoring over time
Monitoring particularly requires comparison of tests performed with comparable protocols.
Is preparation needed
OCT usually needs no special preparation.
Keeping the gaze fixed
The patient sits at the scanner, rests the head on the support and looks at a target.
Eye injury
Urgent ophthalmic care is required. OCT may form part of an urgent examination but must not delay in-person medical assessment.
Limitations and safety
OCT does not replace a comprehensive ophthalmic examination.
The doctor or specialist determines which area needs assessment:macula;the optic disc;nerve fibre layer;anterior segment;vascular bed for OCT angiography.
Takes: 1 minute
Stage 2
Preparation for scanning
The patient sits in front of the scanner.
Takes: 1 minute
Stage 3
Gaze fixation
The patient is asked to look at a light or another fixation target.
Takes: 1 minute
Stage 4
Optical scanning
The scanner acquires a series of scans of the selected area.
Takes: 1 minute
Stage 5
Quality control
The specialist checks:centration;signal quality;artefacts;correct segmentation;completion of the selected protocol.
Takes: 1 minute
Stage 6
Analysis of results
The doctor assesses the images and quantitative measurements.
Takes: 2 minutes
Stage 7
Findings and care plan
The patient receives the examination results.
Takes: 2 minutes
Service benefits
Layer-by-layer tissue images
OCT shows tissue structure and can reveal changes that a routine examination may miss.
Objective structural measurements
Thickness and other measurements help the doctor assess the examined area more precisely.
Imaging without incisions
OCT produces images through optical scanning without surgical access inside the eye.
Tracking changes over time
Comparable repeat examinations reveal changes and help assess prescribed treatment.
Comparison of OCT examination types
Criterion
Macular OCT
Optic disc / RNFL OCT
Anterior-segment OCT
OCT angiography
Main examination area
Macula and central retina
Optic disc, retinal nerve fibre layer (RNFL), and ganglion cells in some protocols
Cornea, anterior chamber, angle and other accessible anterior structures
Microvascular network of the retina, macula, optic disc and other accessible areas
What it shows
Retinal layers, thickness, fluid, membranes, traction, holes and other changes
Optic-disc structure and nerve fibre layer thickness
Anterior-segment anatomy
Vascular network and areas with altered blood-flow signal
macular oedema;
Main method of structural assessment
Not the main purpose
No
May complement structural OCT
Age-related macular degeneration
High clinical importance
Not the main purpose
No
Additional vascular information
Diabetic retinopathy
Assessment of macular oedema and other structural changes
Additional
No
Vascular assessment when indicated
Glaucoma
Macular ganglion-cell analysis may complement assessment
One of the key structural protocols
May complement anterior chamber / angle assessment on a suitable device
Additional research/clinical tool; does not replace standard examination
Optic-nerve disease
Additional assessment of inner macular layers
High importance
No
May complement assessment when indicated
Contrast agent
No
No
No
No
Eye contact
No
No
No
No
Pupil dilation
Not always
Not always
Usually unnecessary
Depends on image quality and protocol
Follow-up over time
Yes
Yes
Yes
Yes
Main limitations
Media opacities, fixation and artefacts
The same, plus optic-disc anatomy and normative-database limitations
Optical and anatomical limitations of the method
Motion and segmentation artefacts and limited visualisation of slow blood flow
Can it replace a doctor’s examination?
No
No
No
No
Macular OCT
Main examination area
What it shows
macular oedema;
Age-related macular degeneration
Diabetic retinopathy
Glaucoma
Optic-nerve disease
Contrast agent
Eye contact
Pupil dilation
Follow-up over time
Main limitations
Can it replace a doctor’s examination?
Macula and central retina
Retinal layers, thickness, fluid, membranes, traction, holes and other changes
Main method of structural assessment
High clinical importance
Assessment of macular oedema and other structural changes
Macular ganglion-cell analysis may complement assessment
Additional assessment of inner macular layers
No
No
Not always
Yes
Media opacities, fixation and artefacts
No
Optic disc, retinal nerve fibre layer (RNFL), and ganglion cells in some protocols
Optic-disc structure and nerve fibre layer thickness
Not the main purpose
Not the main purpose
Additional
One of the key structural protocols
High importance
No
No
Not always
Yes
The same, plus optic-disc anatomy and normative-database limitations
No
Cornea, anterior chamber, angle and other accessible anterior structures
Anterior-segment anatomy
No
No
No
May complement anterior chamber / angle assessment on a suitable device
No
No
No
Usually unnecessary
Yes
Optical and anatomical limitations of the method
No
Microvascular network of the retina, macula, optic disc and other accessible areas
Vascular network and areas with altered blood-flow signal
May complement structural OCT
Additional vascular information
Vascular assessment when indicated
Additional research/clinical tool; does not replace standard examination
May complement assessment when indicated
No
No
Depends on image quality and protocol
Yes
Motion and segmentation artefacts and limited visualisation of slow blood flow
No
OCT and other diagnostic methods
Criterion
OCT
Ophthalmoscopy
Perimetry
Fluorescein angiography
Eye ultrasound
Main information
Structural layered images
Clinical fundus examination
Functional visual field
Vascular dynamics after dye administration
Anatomy using ultrasound
Macula
Highly detailed structure
The doctor sees the surface and clinical changes
Does not show macular anatomy
Useful for assessing leakage and vascular changes
Limited detail
Optic nerve
Structural optic-disc/RNFL parameters
Clinical optic-disc assessment
Functional visual-field assessment
Limited role
May be used for specific tasks
Glaucoma
Structural diagnostic component
Important component
Key functional assessment
Usually not the main method
For specific indications
Retinal vessels
Structural OCT + OCT-A
Visible vascular changes
No
Detailed assessment of circulation and leakage
No comparable detail
Intravenous contrast
No
No
No
Yes
No
Media opacity
Quality may fall substantially
Examination may be difficult
Sometimes possible
Quality may decrease
Ultrasound retains diagnostic value through opaque media
Functional or structural method
Structural
Clinical anatomical
Functional
Vascular
Anatomical
Do the methods replace one another?
No
No
No
No
No
OCT
Main information
Macula
Optic nerve
Glaucoma
Retinal vessels
Intravenous contrast
Media opacity
Functional or structural method
Do the methods replace one another?
Structural layered images
Highly detailed structure
Structural optic-disc/RNFL parameters
Structural diagnostic component
Structural OCT + OCT-A
No
Quality may fall substantially
Structural
No
Clinical fundus examination
The doctor sees the surface and clinical changes
Clinical optic-disc assessment
Important component
Visible vascular changes
No
Examination may be difficult
Clinical anatomical
No
Functional visual field
Does not show macular anatomy
Functional visual-field assessment
Key functional assessment
No
No
Sometimes possible
Functional
No
Vascular dynamics after dye administration
Useful for assessing leakage and vascular changes
Limited role
Usually not the main method
Detailed assessment of circulation and leakage
Yes
Quality may decrease
Vascular
No
Anatomy using ultrasound
Limited detail
May be used for specific tasks
For specific indications
No comparable detail
No
Ultrasound retains diagnostic value through opaque media
Anatomical
No
Book an appointment
Depending on the selected protocol, OCT helps assess the retina, macula, optic nerve and other structures in detail.
Book the examination on an ophthalmologist’s recommendation, or arrange a consultation if you do not know which OCT protocol is needed.
Book OCT
Our services, payable in installmentsTake care of your vision today and pay for our services in installments. Choose installment terms and a payment schedule that suit you.
per eye
The exact OCT fee depends on the area examined and the protocol: macula, optic disc, nerve fibre layer, anterior segment or OCT angiography.
Optical coherence tomography provides cross-sectional and layered images of eye tissues with high spatial resolution.
The method analyses light reflected by tissues.
From the reflected signal, the scanner builds images that allow the doctor to assess anatomy and the thickness of individual layers in the structure being examined.
OCT is particularly useful in retinal and macular disease, glaucoma and optic-nerve disease.
Suitable systems can also examine anterior-segment structures.
What OCT can show
Depending on the selected protocol, the examination helps assess:
retinal thickness;
retinal layer architecture;
the macula;
intraretinal or subretinal fluid;
macular oedema;
epiretinal membranes;
vitreomacular traction;
macular holes;
structural changes in age-related macular degeneration;
changes in diabetic retinopathy;
the optic disc;
the retinal nerve fibre layer;
the ganglion cell complex;
structural changes in glaucoma;
selected anterior-segment parameters.
OCT shows tissue structure; the doctor establishes the diagnosis after comparing the scans with the clinical findings.
Depending on the protocol, OCT can evaluate the macula and retina, optic nerve head, retinal nerve fibre layer and, on appropriate systems, structures of the anterior segment.
OCT is widely used in the diagnosis and follow-up of retinal and macular disease, glaucoma, optic-nerve disorders and other ophthalmic conditions.
OCT does not replace an ophthalmologist consultation.
Its findings should be interpreted by an ophthalmologist together with symptoms, clinical examination and other diagnostic data.
Further procedure details
Preparation for scanning
The patient sits in front of the scanner.
The chin and forehead rest on supports to reduce head movement.
Gaze fixation
The patient is asked to look at a light or another fixation target.
Good fixation helps obtain high-quality scans.
Optical scanning
The scanner acquires a series of scans of the selected area.
The patient usually does not feel the scanning light.
Quality control
The specialist checks:
centration;
signal quality;
artefacts;
correct segmentation;
completion of the selected protocol.
Individual scans are repeated if needed.
Analysis of results
The doctor assesses the images and quantitative measurements.
Results are compared with symptoms, examination findings and previous scans.
Findings and care plan
The patient receives the examination results.
If needed, the doctor may recommend:
Monitoring;
Repeat OCT;
Additional tests
A specialist consultation;
Treatment.
Additional advice and situations
If OCT has been prescribed for the first time
Bring:
a referral or doctor’s report;
previous ophthalmic records;
results of other examinations.
For repeat OCT
Bring previous scans and protocols.
Comparison helps assess changes over time.
If image quality is insufficient
The specialist may:
repeat a scan;
change the protocol;
improve centration;
ask you to change fixation;
recommend pupil dilation;
use another diagnostic method.
If OCT identifies a change
Do not interpret the image yourself.
The doctor determines:
whether monitoring is needed;
whether additional examinations are needed;
whether treatment is required;
how often to repeat OCT.
If OCT is normal but symptoms persist
A normal OCT does not exclude all causes of worsening vision.
The doctor may order:
perimetry;
ophthalmoscopy;
tonometry ;
ultrasound;
angiography;
electrophysiological examinations;
other tests as indicated.
Further information
OCT must be interpreted correctly, not just performed
A modern scanner produces many images, maps and measurements.
They gain diagnostic value through medical interpretation.
The ophthalmologist assesses:
Scan quality;
Eye anatomy;
Patient age;
Degree of myopia;
Optic disc condition;
Associated conditions;
Previous tests;
Changes over time;
The patient's symptoms.
Facts and offers
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.