
Monofocal intraocular lenses (IOLs)
A monofocal IOL has one principal optical focus.
Learn moreA monofocal IOL has one principal optical focus.
Learn moreA toric IOL replaces the lens while correcting corneal astigmatism.
Learn moreA multifocal IOL provides several optical foci to reduce dependence on glasses at different distances.
Learn moreIOL selection involves assessing eye health, biometry and lens-power calculation. The doctor discusses desired vision at different distances and an appropriate optical option.
Patients with cataract who are preparing for phacoemulsification and need IOL power calculation.
Patients with regular corneal astigmatism who may benefit from a toric IOL.
People prioritising high-quality distance vision and who accept reading spectacles if needed. Patients seeking less spectacle dependence at intermediate or multiple distances and willing to discuss EDOF, multifocal or trifocal designs.
Patients after LASIK, PRK, SMILE, radial keratotomy or other corneal surgery where IOL calculations require additional care.
Patients with retinal, macular, optic-nerve or corneal disease where the range of suitable optical designs must be determined first.
Patients planning second-eye surgery when the target can be refined using the first-eye result.
No IOL fully reproduces a young natural crystalline lens or guarantees freedom from glasses. Premium optical designs may cause halos, glare and light scatter and require neuroadaptation. Macular or optic nerve disease, marked corneal changes, irregular astigmatism, an unstable tear film or other disorders may limit the range of suitable lenses.
Toric IOLs require accurate astigmatism assessment and axis alignment; postoperative rotation can reduce correction.
IOL calculations are more difficult after prior corneal refractive surgery or radial keratotomy, and residual refractive error is less predictable.
Bring previous examination results and information about all eye operations, particularly LASIK, Femto LASIK, PRK, TransPRK, SMILE, keratotomy, vitrectomy and retinal surgery. Tell the doctor how important night driving, computer work, small print, sport, occupational visual demands and reducing dependence on glasses are to you.
If you wear contact lenses, confirm with KazRIED how long they should be discontinued before keratometry and biometry because the interval depends on lens type and corneal condition.
After lens surgery, urgent review is required for sudden visual loss, severe pain, marked redness, flashes, a curtain-like shadow or rapidly increasing floaters.
No IOL fully recreates the accommodation of a young natural lens or guarantees spectacle independence.
Book a consultation
The surgeon clarifies priority distances and activities and the patient’s willingness to use spectacles.

Cataract is confirmed and the cornea, anterior segment, intraocular pressure, retina and optic nerve are evaluated.

Baseline refraction and corneal astigmatism are measured for calculation and toric planning.
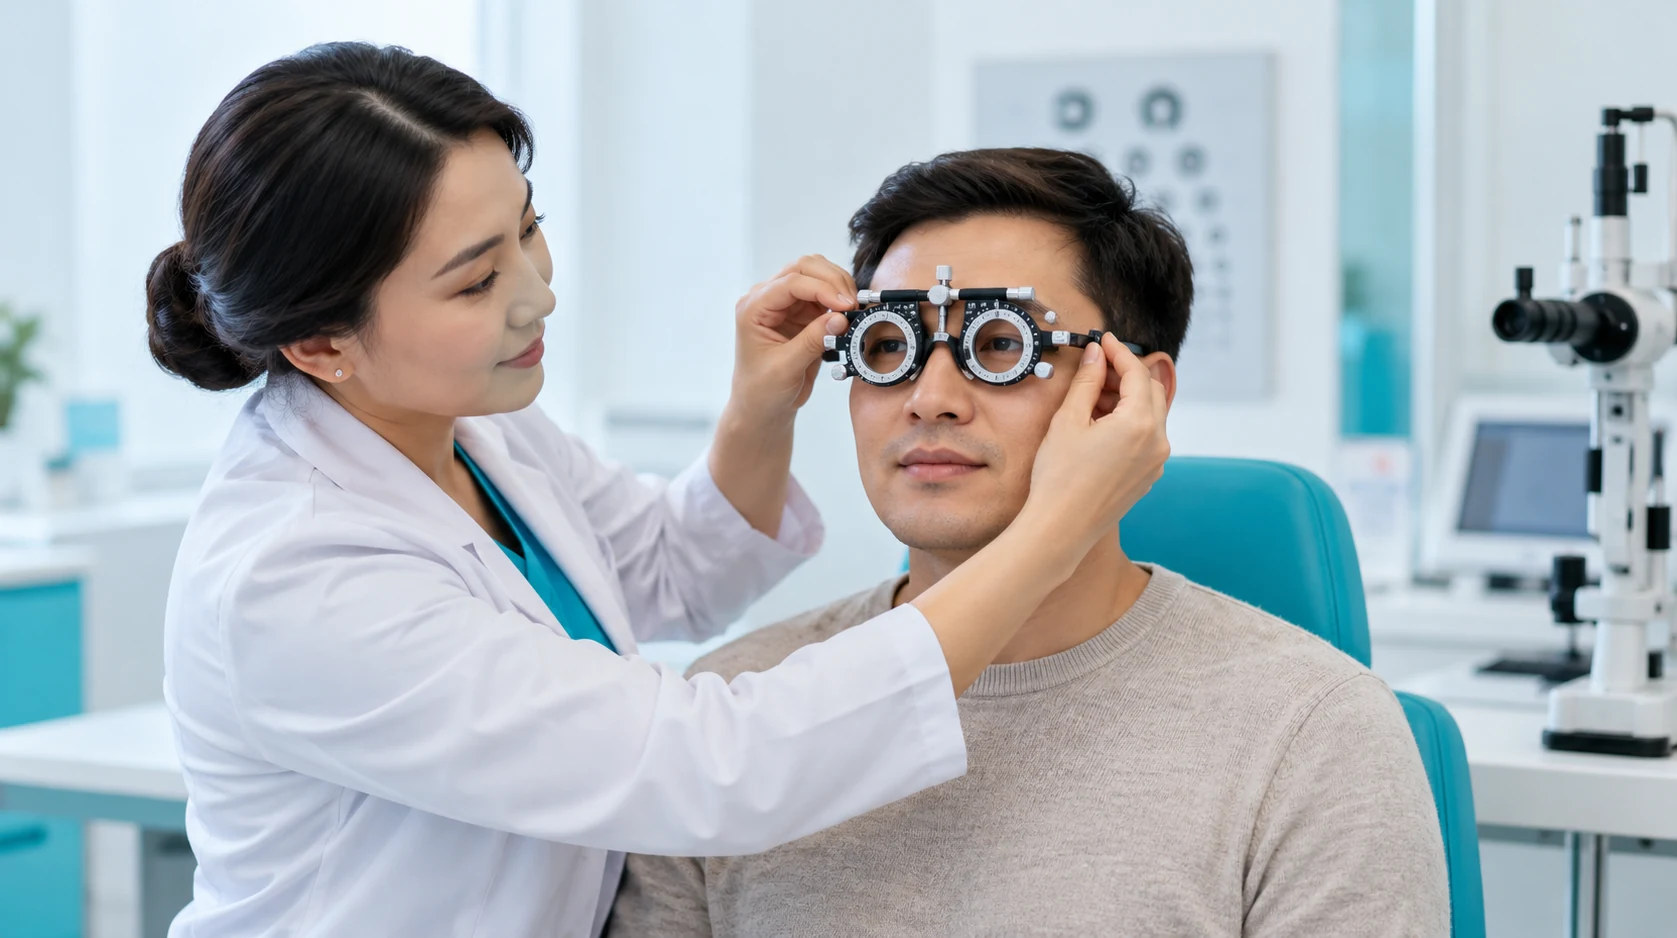
IOL Master / ARGOS or ultrasound calculation is used as indicated; the price list includes a separate multifocal-IOL calculation.
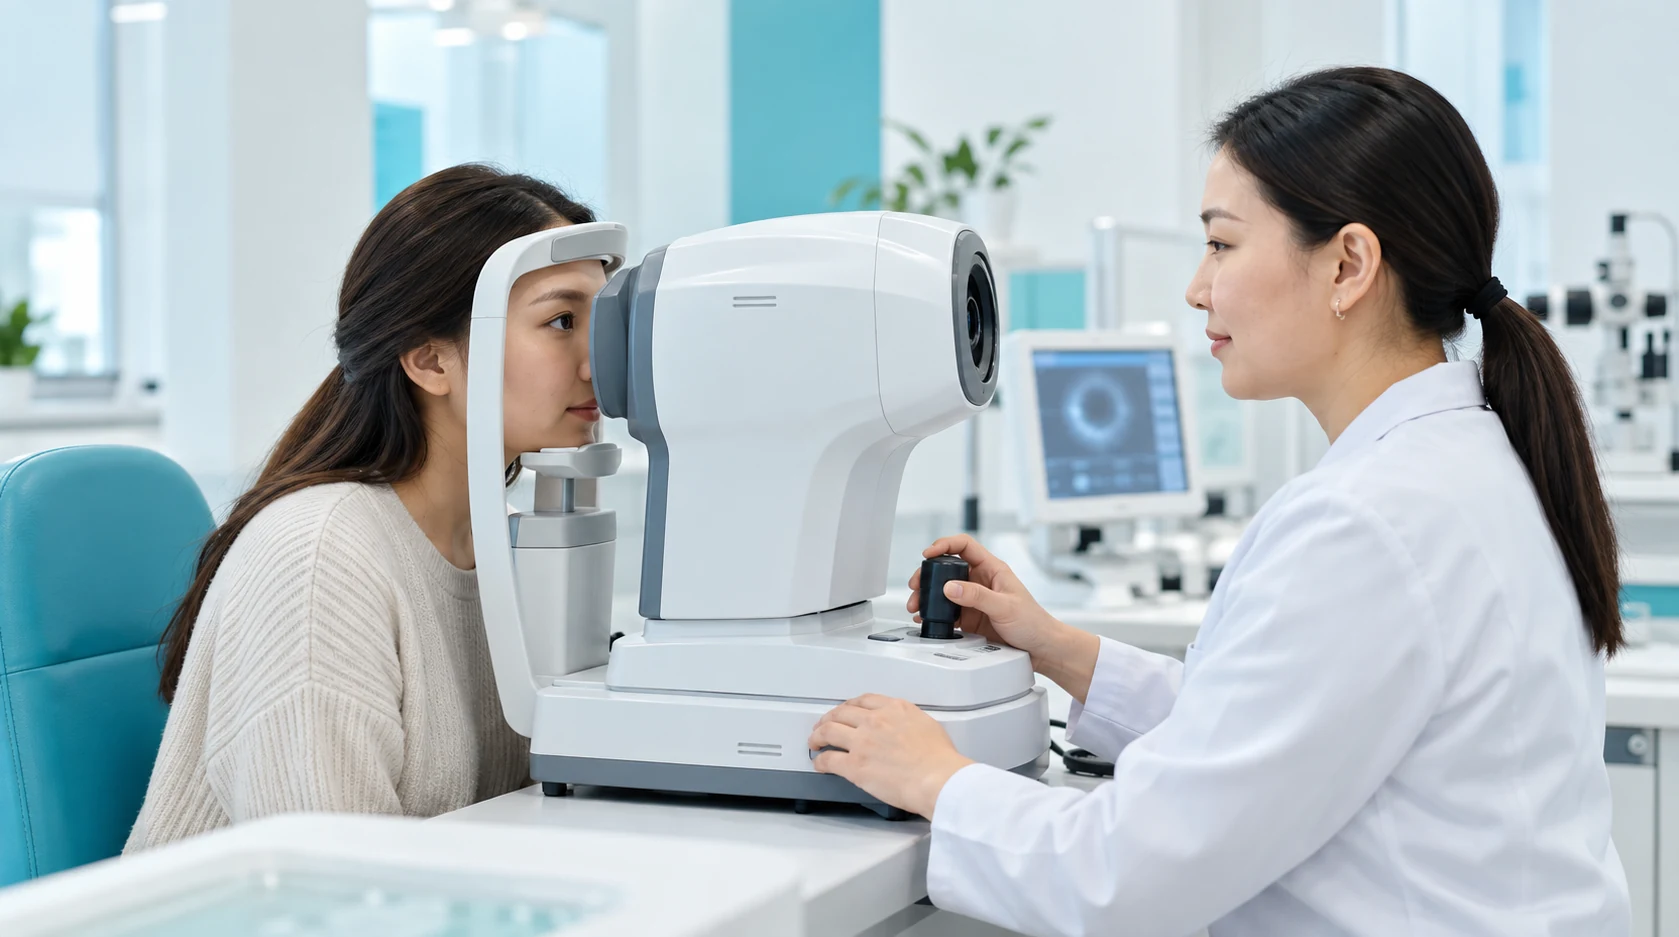
Corneal topography/tomography, macular OCT, ultrasound or other tests are added when clinically relevant.
Monofocal, toric, enhanced monofocal, EDOF and multifocal/trifocal options are compared against ocular limitations and goals.

The surgeon checks the selected model, lens power, correct eye, refractive target and surgical plan.

IOL selection takes into account the distance at which seeing without glasses matters most to the patient.
Biometry helps calculate artificial lens power using the eye's individual measurements.
Corneal measurements help determine whether a toric IOL is needed to correct regular astigmatism.
Optics are selected according to retinal, corneal and optic nerve health, with the model's benefits and limitations discussed.
After measurements, the surgeon can help choose the most appropriate IOL strategy rather than simply the most premium lens, taking into account ocular health, astigmatism, distance/intermediate/near priorities and the possibility that spectacles may still be useful.
A team of experienced doctors across specialties.

Candidate of Medical Sciences; Highest-category ophthalmologist

Candidate of Medical Sciences; Highest-category ophthalmologist

Candidate of Medical Sciences; Highest-category ophthalmologist

Doctor of Philosophy (PhD)

Highest-category ophthalmologist

Highest-category ophthalmologist

Highest-category ophthalmologist

Highest-category ophthalmologist

Highest-category ophthalmologist

Highest-category ophthalmologist
Selecting an intraocular lens (IOL) involves two related tasks: calculating its optical power and choosing its optical design.
The first task is to measure the eye and calculate the lens power intended to bring the postoperative refraction close to the chosen target.
This involves biometry and keratometry, with additional examinations of the cornea and posterior segment in complex cases.
The most expensive lens is not necessarily the best for an individual eye. The right choice is based on anatomy, coexisting conditions, and the patient’s actual visual needs.
Additional assessment is particularly useful in cases of significant astigmatism, high myopia or hyperopia, previous laser vision correction, keratotomy, macular or optic nerve disease, diabetic retinopathy, an irregular cornea, previous vitreoretinal surgery, or when the patient is considering an EDOF, multifocal, or trifocal IOL.
For the second eye, the target refraction and strategy may be refined according to the first eye’s outcome and the visual balance between the eyes.
SENSAR AAB00: a single-piece posterior chamber IOL.
An aspheric monofocal IOL.
An aspheric hydrophobic acrylic IOL.
A toric enhanced monofocal IOL.
A trifocal / multifocal IOL.
A toric trifocal / multifocal IOL.
A presbyopia-correcting IOL.
A toric presbyopia-correcting IOL.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.
Kazakhstan’s first specialized ophthalmology institute, operating since 1933.
Modern diagnostics and surgery using world-class equipment.
Leading ophthalmologists in Kazakhstan, scientists and experienced surgeons.
More than 30,000 operations and around 270,000 consultations annually.


